Long-term effects of COVID-19 in patients according to the functional lung imaging in radiation therapy


















DOI: 10.32364/2587-6821-2022-6-7-360-366
V.P. Zolotnitskaya, A.A. Speranskaya, N.A. Kuzubova, O.N. Titova, O.V. Amosova
I.P. Pavlov First St. Petersburg State Medical University, St. Petersburg, Russian Federation
Background: the majority of patients who experienced COVID-19, lung disorders persist for a long term. It remains unclear how reversible they are and what the clinical and radiation predictors of these changes are.
Aim: to determine the consequences of pneumonia caused by the SARS-CoV-2 virus in patients who experienced COVID-19 during the period of 2020–2021; to evaluate possible clinical and radiation predictors of these changes and their reversibility.
Patients and Methods: the article presents the analyzed results of radiation studies (computed tomography (CT), single-photon emission computed tomography (SPECT)), spirometry and diffusing capacity of the lungs for carbon monoxide (DLCO) performed in 68 patients who had COVID-19 during the period of 2020–2021 and complained of persistent shortness of breath, fatigue and disability.
Results: 1–2 years after, there was a decrease in the bronchial patency to 39.2±4.5%pred in 63% of patients with mild COVID-19, which correlated (rs>0.92) with a decrease in microcirculation (MC) over 50% and mosaic attenuation (rs>0.77), air trapping (rs>0.89) and bronchiolectasis (rs>0.64). In mixed ventilatory defects (MEF75 to 46.8±3.6% of predicted, DLCO 62.4±3.1% of predicted), there were significant MC disorders over 70%, corresponding to zones of focal pneumosclerosis (rs>0.93). In the severe disease course, single areas of "frosted glass" were detected in 13% of patients, while mosaic attenuation and air trapping were detected in 34%, which was accompanied by a decrease in MEF75 to 37.4±3.7% of predicted. During a decrease in DLCO to 52.4±2.2% of predicted, there were a compaction of the interstitial by the type of usual interstitial pneumonia of small extent (65%), consolidation areas (34%), pneumosclerosis areas (54%), platelike atelectasis (31%), bronchiectasis (26%), signs of bronchiolitis obliterans (42%), and pulmonary hypertension development (38%). According to the single-photon emission computed tomography data, there were significant disorders of the MC. Irreversible changes were detected in lung areas with an inadequate perfusion of more than 50%, observed 6 months after the disease, and subsequently, after 1 year or more.
Conclusions: a comprehensive functional lung imaging in radiation therapy increases the efficacy of clinical examination of patients in the postcovid period. The following type of patients need a comprehensive radiation monitoring: patients over 60 y.o., patients who had a severe COVID-19; patients who have respiratory complaints over 1 year, regardless of the COVID-19 severity. Microcirculation disorders over 50% detected 6 months after the disease are a predictor of changes in the lung parenchyma and may indicate long-term disease consequences.
Keywords: postcovid syndrome, microcirculation, computed tomography of the lungs, ventilation, artificial intelligence.
For citation: Zolotnitskaya V.P., Speranskaya A.A., Kuzubova N.A. et al. Long-term effects of COVID-19 in patients according to the functional lung imaging in radiation therapy. Russian Medical Inquiry. 2022;6(7):360–366 (in Russ.). DOI: 10.32364/2587-6821-2022-6-7-360-366.
Background
The fight against the COVID-19 infection remains an important issue. The disease is characterized by atypical viral pneumonia involving the bronchioles, alveoli, and small vessels. As a result, pulmonary gas exchange is strongly affected. Less oxygen enters the blood, thereby resulting in hypoxia and altering the functions of the entire organism. Additionally, pulmonary damage by SARS-CoV-2 impairs surfactant synthesis, which contributes to irreversible changes in the lung parenchyma, including scarring (fibrosis) [1–4].
To date, immediate results of chest computed tomography (CT) after the COVID-19 infection have been largely described [5–8]. In 94% of patients discharged from the intensive care unit (ICU), lung parenchymal lesions (typically ground-glass opacities) are reported. Foreign and domestic researchers claim that lung lesions, i.e., residual ground-glass opacities, pulmonary consolidation, parenchymal cords, perilobular opacities, traction bronchiectasis/bronchiolectasis, fibrosis (reticulations, thickening of the interlobular septa, honeycombs), irregular ventilation/air traps, and mosaic perfusion persist in 35%-48% and 24%–27% of patients, respectively, 6 and 12 months after recovery [1, 9–12]. Moreover, it is unclear whether these changes are reversible and whether they can be further predicted.
Additionally, patients who experience a severe COVID-19 infection are followed up and examined for a long time. Generally, patients managed in an outpatient setting do not undergo chest imaging. Meanwhile, some of these patients complain of fatigue, dyspnea, headache, muscle and joint pain for over a year after the disease [2, 13].
By the end of influenza A (H1N1)- and SARS-CoV-related pneumonia outbreak, long-term examination revealed residual pulmonary lesions (focal and multifocal fibrosis, consolidation, traction bronchiectasis, interlobular indurations, honeycombs, etc.) in 4% [14, 15]. Since SARS-CoV-2 nucleocapsid protein shares more than 90% homology with SARS-CoV-1 protein [16], similar outcomes can be expected after the COVID-19 pandemic. Given that the number of registered patients who have recovered from the COVID-19 infection in Russia is almost 2 million, this can add a further burden to the healthcare system. Current knowledge on clinical and radiological predictors of pulmonary lesions in SARS-CoV-2 pneumonia survivors and their long-term consequences is scarce [17].
Aim
To describe SARS-CoV-2 pneumonia outcomes in patients who experienced the COVID-19 infection in 2020–2021 to determine their potential clinical and radiological predictors and reversibility.
Patients and Methods
We analyzed chest CT scans of 68 patients (21 men and 47 women, mean age 68.7 ± 15.4 years) who recovered from the COVID-19 infection in 2020–2021. These patients were examined to detect abnormalities in pulmonary circulation and disease complications.
Patients who experienced the COVID-19 infection more than a year ago, verified by medical records and complained of persistent shortness of breath, weakness, and inability of performing fully work activities were included in the study. All patients were divided into two groups based on the severity of primary lung lesions by multislice CT (MSCT). Group 1 included 30 patients with CT-1 or CT-2 pneumonia and group 2 included 38 patients with CT-3 or CT-4 pneumonia.
Exclusion criteria were mechanical ventilation in the acute phase, chronic lung diseases, congestive heart failure, age under 18, severe liver and kidney failure, and malignancies.
All patients underwent MSCT, single-photon emission computed tomography (SPECT), and spirometry. Additionally, the diffusing capacity of the lung for carbon monoxide (DLCO) was measured. These tests were performed 6 months, 9 months, and 1 year or more (up to 2 years) after disease onset. All patients or their representatives signed informed consent for medical examination. Lung SPECT perfusion imaging was performed using the Philips Forte Gamma Camera (standard Lung Spect protocols). High-resolution chest CT was performed using 16 and 64-slice GE CT scanners using standard technique.
The key goal of lung SPECT perfusion imaging is to identify the severity of microcirculatory (MC) abnormalities after the COVID-19 infection using artificial intelligence/AI (lung perfusion scintigraphy image analyzer/LungScintAnalyser) [18]. MC abnormalities were estimated. The intensity of the accumulation of radiopharmaceutical (RP) γ-quanta on the scintigram was assessed using a color scale as a distance from normal values (a decrease was marked in blue, an increase in red). Normal values ranged from 0.85 to 1.15 (hypoperfusion 0.3–0.7, hyperperfusion ≥1.3). Values <0.3 were considered an accumulation defect.
MSCT was performed using an AI-based density mask protocol to precisely assess the percentage of lung tissue damage and how widespread lesions are.
Statistical analysis was performed using the Statistica 10 software. Patient characteristics were analyzed using descriptive statistics methods. Data are represented as the arithmetic mean (M) and standard error of the mean (m). Associations between parameters were evaluated using Spearman’s rank correlation coefficient (rs). The relationship was considered strong at rs >0.7, medium at rs 0.3–0.7, and weak at rs <0.3.
Results
In 19 patients who experienced mild-to-moderate COVID-19, a significant obstruction of the smaller bronchi only was revealed when analyzing spirometry test results at the time of lung SPECT. The maximum expiratory flow rate at 75% of FVC (MEF75) was 39.2±4.5% and correlated greatly (rs>0.92) with MC abnormalities in the upper lobes of the lungs. MC disorders with RP accumulation less than half of the norm correlated greatly with mosaic perfusion zones (rs>0.77) and air traps (rs>0.89). MC disorders with RP accumulation less than a third of the norm correlated greatly with bronchiolectasis (rs>0.64) detected by MSCT.
In 11 patients, mixed obstruction of the smaller bronchi (MEF75 46.8±3.6%, DLCO 62.4±3.1%) was revealed. Lung SPECT detected reduced MC in the upper lobes of the lungs and local subsegmental perfusion defects. When comparing the results of SPECT and MSCT, abnormal perfusion of the upper lobes of the lungs correlated greatly with local areas of distension (rs>0.84) and thickening of small bronchial walls (rs>0.87). Local areas of hypoperfusion (<30% of the norm) corresponded to the areas of local pulmonary fibrosis (rs>0.93).
The severe COVID-19 infection survivors underwent MSCT over time. Lung parenchymal lesions persisted 3 to 6 months after discharge. The most common lesions were ground-glass opacities (94%), nonspecific interstitial pneumonia-like interlobular interstitial compaction or limited classic interstitial pneumonia (41%), pulmonary consolidations (32%), residual lesions of large and small bronchi (traction, traction bronchiectasis, bronchiolectasis, signs of bronchiolitis obliterans, 29%), and residual vascular abnormalities (mosaic perfusion, pulmonary hypertension/PH, 16%). MSCT performed 1 year or more after recovery has demonstrated that single ground-glass opacities were detected in 5 patients (13%), while mosaic ventilation and air traps were identified in 14 patients (34%). This phenomenon is accompanied by the obstruction of small bronchi (MEF75 37.4±3.7%). In 20 patients, limited classic interstitial pneumonia-like interlobular interstitial compaction (65%), pulmonary consolidations (34%), areas of pulmonary fibrosis (54%), discoid atelectasis (31%), bronchiectasis (26%), signs of obliterating bronchiolitis (42%), and PH (38%) were identified. A significant decrease in DLCO (52.4±2.2%) was reported. Lung SPECT detected significant MC abnormalities, which were quantitatively (in %) greater than those detected by MSCT (see Fig. 1). Chest CT using a density mask protocol performed 1 to 1.5 years later has demonstrated an increase (by 16.3±2.4%) in lung parenchymal lesions. Perfusion abnormalities correlated greatly (rs>0.98) with RP accumulation less than half of the norm. Later, permanent lesions emerged in these areas.
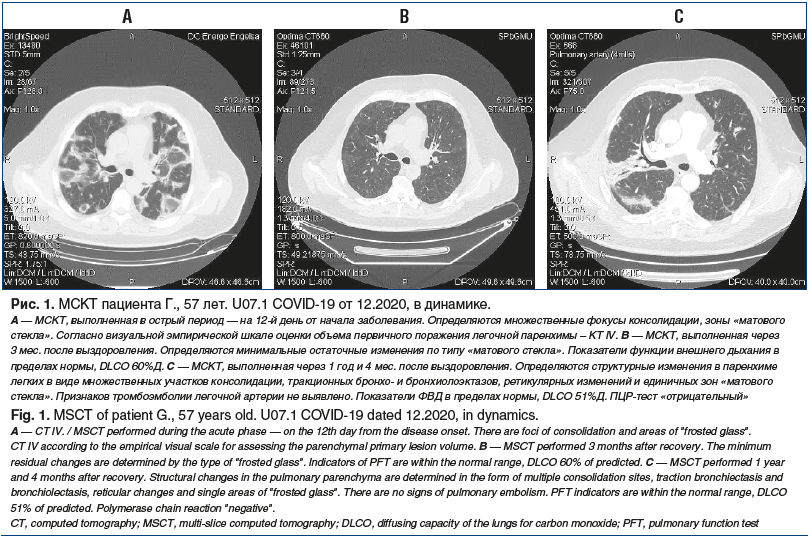
We describe a 57-year-old man with virus-associated interstitial lung disease (ILD). MSCT scans over time (see Fig. 1), MC abnormalities (see Fig. 2), and AI-based MSCT scan processing (see Fig. 3) are addressed. This case report illustrates the effects of MC abnormalities on the evolution of pulmonary lesions by comparing lung SPECT and chest CT scans.
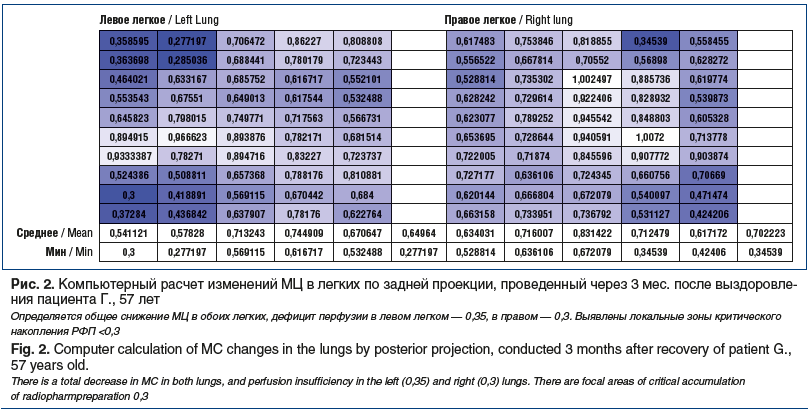
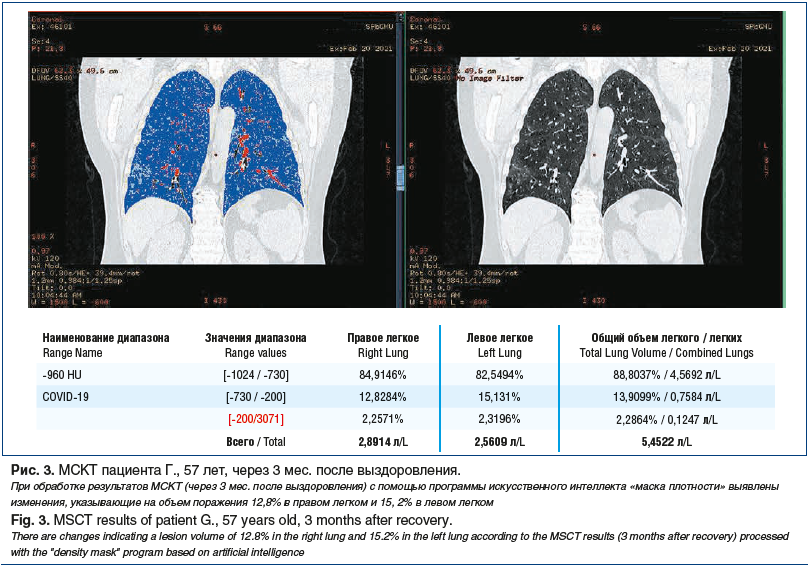
The analysis the of SPECT has demonstrated that MC abnormalities are predictors of structural lesions of the lung parenchyma.
Discussion
Our study has demonstrated that in patients with SARS-CoV-2-associated pneumonia and complaints of dyspnea, poor performance, and fatigue for more than a year, the obstruction of small bronchi is detected. This obstruction indicates damage to the respiratory area and the development of interstitial lung disease associated with a significant reduction in diffusing capacity. Complex radiological examination (lung SPECT and chest MSCT) revealed structural lesions of the lung parenchyma and MC disorders. Unfortunately, at the time of writing, we failed to find any studies on blood circulation abnormalities in lungs a year or more after the COVID infection or studies comparing these data and MSCT, spirometry, and DLCO results. Published data [19–21] demonstrate persistent severe respiratory failure for more than 6 months after discharge from the ICU. Meanwhile, pathological chest CT findings are still detected after the acute phase in 76%.
To compare, earlier published data on long-term outcomes in patients with SARS-associated pneumonia can be addressed. A year after discharge, abnormal DLCO was reported in most patients (80%). These abnormalities were mild in 46% and moderate in 23%. Restrictive and obstructive respiratory disorders were found in 20%. Obstruction most commonly occurs among smokers [22]. In a prospective cohort study by D.S. Hui et al. [23] involving 110 survivors of acute lung injury (ALI)/acute respiratory distress syndrome (ARDS) caused by SARS, low DLCO persisted in 24% and radiological changes in 28% one year after disease onset. H. Shi et al. [24] reported that chest CT scans after 6 months demonstrate pulmonary fibrosis in more than a third of patients with severe COVID-19-associated pneumonia. These abnormalities correlated with older age, ARDS development, long hospital stay, tachycardia, noninvasive ventilation, and high chest CT lesions at baseline. Given the course of other coronavirus infections, e.g., SARS and Middle East Respiratory Syndrome (MERS), postinfectious pulmonary fibrosis can be suggested [25]. Pulmonary fibrosis and persistent pathological chest CT findings occur up to 7 years after symptom onset [26].
Certainly, in most patients, lung parenchymal lesions completely disappear over time or minimal pulmonary fibrosis persists [5]. V. D'Onofrio et al. has demonstrated that extensive chest CT abnormalities that are initially interpreted as fibrosis (reticular anomalies, bronchial traction, transseptal consolidations) either disappear completely or become significantly smaller over time. Therefore, these lesions cannot be regarded as a fibrotic transformation [27]. However, we still follow-up patients who report on subjective worsening in their physical and functional performance more than a year after the disease. The MC abnormalities, lung parenchymal lesions, and external respiration parameters persist in these patients. These patients should undergo imaging procedures (MSCT, SPECT) and lung function evaluation (spirometry, diffusing capacity) in the long-term period (1 year or more) after the disease.
Age over 60 and severity of viral pneumonia are particularly important. We do not discuss the results of imaging in patients with chronic lung diseases and patients who experienced pulmonary embolism during the disease.
Conclusions
1. Comprehensive pulmonary function imaging tests increase the efficacy of medical examination in the post-COVID period.
2. Patients over 60, survivors of severe COVID-19 infection, and patients with persistent respiratory complaints for more than a year, irrespective of COVID-19 severity, require comprehensive radiation examination.
3. MC abnormalities >50% identified 6 months after the disease are predictors of lung parenchymal lesions and evidence of serious complications.
About the authors:
Valentina P. Zolotnitskaya — Dr. Sc. (Bio.), Senior Researcher at the I.P. Pavlov First St. Petersburg State Medical University; 6–8, Lev Tolstoy str., St. Petersburg, 197022, Russian Federation; ORCID iD 0000-0002-7982-3805.
Alexandra A. Speranskaya — Dr. Sc. (Med.), Professor of the Department of Radiology and Radiation Medicine with X-Ray and Radiological Departments, I.P. Pavlov First St. Petersburg State Medical University; 6–8, Lev Tolstoy str., St. Petersburg, 197022, Russian Federation; ORCID iD 0000-0001-8322-4509.
Natalia A. Kuzubova — Dr. Sc. (Med.), Head of the Laboratory of the COPD Research Institute of Pulmonology, I.P. Pavlov First St. Petersburg State Medical University; 6–8, Lev Tolstoy str., St. Petersburg, 197022, Russian Federation; ORCID iD 0000-0002-1166-9717.
Olga N. Titova — Dr. Sc. (Med.), Professor, Director of the Research Institute of Pulmonology, I.P. Pavlov First St. Petersburg State Medical University; 6–8, Lev Tolstoy str., St. Petersburg, 197022, Russian Federation; ORCID iD 0000-0003-4678-3904.
Olga V. Amosova — Resident of the Department of Radiology and Radiation Medicine, I.P. Pavlov First St. Petersburg State Medical University; 6–8, Lev Tolstoy str., St. Petersburg, 197022, Russian Federation; ORCID iD 0000-0003-2482-7435.
Contact information: Valentina P. Zolotnitskaya, e-mail: zolotnitskaja68@yandex.ru.
Financial Disclosure: the authors have no financial or property interest in any material or method mentioned.
There is no conflict of interests.
Received 09.07.2022.
Revised 02.08.2022.
Accepted 25.08.2022.
2. Martini K., Larici A.R., Revel M.P. еt al. COVID‑19 pneumonia imaging follow‑up: when and how?A proposition from ESTI and ESR. Eur Radiol. 2022;32(4):2639–2649. DOI: 10.1007/s00330-021-08317-7.
3. Zu Z.Y., Jiang M.D., Xu P.P. et al. Coronavirus disease 2019 (COVID-19): a perspective from China. Radiology. 2020;296(2):E15–E25. DOI: 10.1148/radiol.2020200490.
4. McDonald L.T. Healing after COVID-19: are survivors at risk for pulmonary fibrosis? Am J Physiol Lung Cell Mol Physiol. 2021;320(2):L257–L265. DOI: 10.1152/ajplung.00238.2020.
5. Speranskaya А.А., Osipov N.P., Lyskova Yu.А., Amosova O.V. CT patterns of residual changes in COVID-19 lung lesions. Diagnostic radiology and radiotherapy. 2021;12(4):58–64 (in Russ.). DOI: 10.22328/2079-5343-2021-12-4-58-64.
6. Pershina E.S., Cherniaev A.L., Samsonova M.V. et al. Comparison of the СT patterns and pulmonary histology in patients with COVID-19. Medical Visualization. 2020;24(3):37–53 (in Russ.). DOI: 10.24835/1607-0763-2020-3-37-53.
7. Fang Y., Zhang H., Xie J. et al. Sensitivity of Chest CT for COVID-19: Comparison to RT-PCR. Radiology. 2020;296(2):E115–E117. DOI: 10.1148/radiol.2020200432.
8. Pan F., Ye T., Sun P. et al. Time Course of Lung Changes at Chest CT during Recovery from Coronavirus Disease 2019 (COVID-19). Radiology. 2020;295(3):715–721. DOI: 10.1148/radiol.2020200370.
9. Han X., Fan Y., Alwalid O. et al. Six-month Follow-up Chest CT Findings after Severe COVID-19 Pneumonia. Radiology. 2021;299(1):E177–E186. DOI: 10.1148/radiol.2021203153.
10. Lerum T.V., Aaløkken T.M., Brønstad E. et al. Dyspnoea, lung function and CT findings 3 months after hospital admission for COVID-19. Eur Respir J. 2021;57(4):2003448. DOI: 10.1183/13993003.03448-2020.
11. Yang Z.L., Chen C., Huang L. et al. Fibrotic Changes Depicted by Thin-Section CT in Patients With COVID-19 at the Early Recovery Stage: Preliminary Experience. Front Med (Lausanne). 2020;7:605088. DOI: 10.3389/fmed.2020.605088.
12. Revel M.P., Parkar A.P., Prosch H. et al. COVID-19 patients and the radiology department — advice from the European Society of Radiology (ESR) and the European Society of Thoracic Imaging (ESTI). Eur Radiol. 2020;30(9):4903–4909. DOI: 10.1007/s00330-020-06865-y.
13. Froidure A., Mahsouli A., Liistro G. et al. Integrative respiratory follow-up of severe COVID-19 reveals common functional and lung imaging sequelae. Respir Med. 2021;181:106383. DOI: 10.1016/j.rmed.2021.106383.
14. Wigén J., Löfdahl A., Bjermer L. et al. Converging pathways in pulmonary fibrosis and Covid-19 — The fibrotic link to disease severity. Respir Med X. 2020;2:100023. DOI: 10.1016/j.yrmex.2020.100023.
15. Avdeev S.N., Karchevskaya N.A., Baimakanova G.E, Cherniak A.V. One year follow up of patients with acute lung injury / acute respiratory distress syndrome caused by influenza A / H1N1 virus. Pulmonology. 2011;4:58–66 (in Russ.).
16. Tilocca B., Soggiu A., Sanguinetti M. et al. Comparative computational analysis of SARS-CoV-2 nucleocapsid protein epitopes in taxonomically related coronaviruses. Microbes Infect. 2020;22(4–5):188–194. DOI: 10.1016/j.micinf.2020.04.002.
17. Samsonova M.V., Kontorschikov A.S., Cherniaev A.L. et al. Long-term pathological changes in lungs after COVID-19. Pul’monologiya. 2021;31(5):571–579 (in Russ). DOI: 10.18093/0869-0189-2021-31-5-571-579.
18. Tishkov A.V., Zolotnitskaya V.P., Amosov V.I. Perfusion lung scintigraphy image analyzer (LungScintAnalyser). Computer program No. 2016615201. 05.23.2016 (in Russ.).
19. Averyanov A.V., Divakova T.I., Balionis O.I. et al. Post-COVID Lung Tissue Damage with Respiratory Failure: Are There Any Therapeutic Tools? Practical pulmonology. 2021;3:11–14 (in Russ.). DOI: 10.24412/2409-6636-2021-12416.
20. Cares-Marambio K., Montenegro-Jiménez Y., Torres-Castro R. et al. Prevalence of potential respiratory symptoms in survivors of hospital admission after coronavirus disease 2019 (COVID-19): A systematic review and meta-analysis. Chron Respir Dis. 2021;18:14799731211002240. DOI: 10.1177/14799731211002240.
21. Sonnweber T., Tymoszuk P., Sahanic S. et al. Investigating phenotypes of pulmonary COVID-19 recovery: A longitudinal observational prospective multicenter trial. Elife. 2022;11:e72500. DOI: 10.7554/eLife.72500.
22. Orme J.Jr., Romney J.S., Hopkins R.O. et al. Pulmonary function and health-related quality of life in survivors of acute respiratory distress syndrome. Am J Respir Crit Care Med. 2003;167(5):690–694. DOI: 10.1164/rccm.200206-542OC.
23. Hui D.S., Wong K.T., Ko F.W. et al. The 1-year impact of severe acute respiratory syndrome on pulmonary function, exercise capacity, and quality of life in a cohort of survivors. Chest. 2005;128(4):2247–2261. DOI: 10.1378/chest.128.4.2247.
24. Shi H., Han X., Zheng C. Evolution of CT Manifestations in a Patient Recovered from 2019 Novel Coronavirus (2019-nCoV) Pneumonia in Wuhan, China. Radiology. 2020;295(1):20. DOI: 10.1148/radiol.2020200269.
25. Antonio G.E., Wong K.T., Hui D.S. et al. Thin-section CT in patients with severe acute respiratory syndrome following hospital discharge: preliminary experience. Radiology. 2003;228(3):810–815. DOI: 10.1148/radiol.2283030726.
26. Wu X., Dong D., Ma D. Thin-Section Computed Tomography Manifestations During Convalescence and Long-Term Follow-Up of Patients with Severe Acute Respiratory Syndrome (SARS). Med Sci Monit. 2016;22:2793–2799. DOI: 10.12659/msm.896985.
27. D’Onofrio V., Keulen L., Vandendriessche A. et al. Studying the clinical, radiological, histological, microbiological, and immunological evolution during the different COVID-19 disease stages using minimal invasive autopsy. Sci Rep. 2022;12(1):1360. DOI: 10.1038/s41598-022-05186-y.

This work is licensed under a Creative Commons «Attribution» 4.0 License.
